Dental revenue cycle management, worked daily.
Submission, follow-up, denial rework and payment posting, handled every day inside your practice management system, not batched up at month end.

- D2740Delta DentalNarrative and x-ray attachedSubmitted
- D4341CignaPerio chart attachedSubmitted
- D0330MetLifeFrequency checkedVerified
- D2950AetnaDenied, reason code readResubmitted
- D1110GuardianERA receivedPosted
- Five locations, two regions
- Live on Dentrix Ascend for My Hometown Dentist and Kona Coast Dental Care. Count the locations on their own sites.
- A BAA before any access
- Signed before anyone touches patient data, every time, without being asked for it.
- Bilingual, on your clock
- Working live through your business day, inside the practice management system you already run.
Built for practices that stopped chasing claims
Most practices do not have a billing problem. They have a follow-up problem. Claims go out fine; then nobody has an uninterrupted hour to chase the ones that stall, so the aging report grows quietly until somebody writes it off.
- 01
Submitted clean
Claims checked against the payer's requirements before they go out, with attachments and narratives attached, because the cheapest denial is the one that never happens.
- 02
Followed up daily
Every claim tracked Open → Pending → Closed. Stalled claims get worked on a fixed cycle rather than whenever someone finds a spare hour.
- 03
Denials reworked
Denials are diagnosed by reason code, corrected and resubmitted. A denial is a step in the process, not the end of it. Most are recoverable if somebody actually works them.
A claim, end to end
Five steps, every day, inside your system. Most of the money is lost at the first and the last.
Verify
Benefits confirmed before the visit
Eligibility, frequencies, history and remaining maximum, checked days ahead and entered in your system.
Insurance verification
Code
Documented the way the payer reads it
Your clinicians code. We check the claim against the payer's rules and attach what the code needs.
Revenue cycle management
Submit
Sent the same day
Clean claims go out daily with x-rays, charting and narratives attached, not batched at the end of the week.
Revenue cycle management
Follow up
Chased before it stalls
Every open claim worked on a fixed cycle. Denials corrected and resubmitted by reason code.
A/R recovery
Post
Paid, posted, and the patient billed right
Payments posted against the fee schedule, underpayments caught, and patient balances billed from an estimate that held.
Revenue cycle management
See every claim and every dollar
Every claim we touch and every dollar we recover shows up on a dashboard you can open yourself. Same data we run the desk on, including the parts that make us look slow.
- Claim lifecycle: Open → Pending → Closed, with the exact claims sitting past ninety days.
- Aging worked down bucket by bucket, reported weekly rather than summarized quarterly.
- Denials grouped by reason code, so you can see which payer and which code is costing you most.
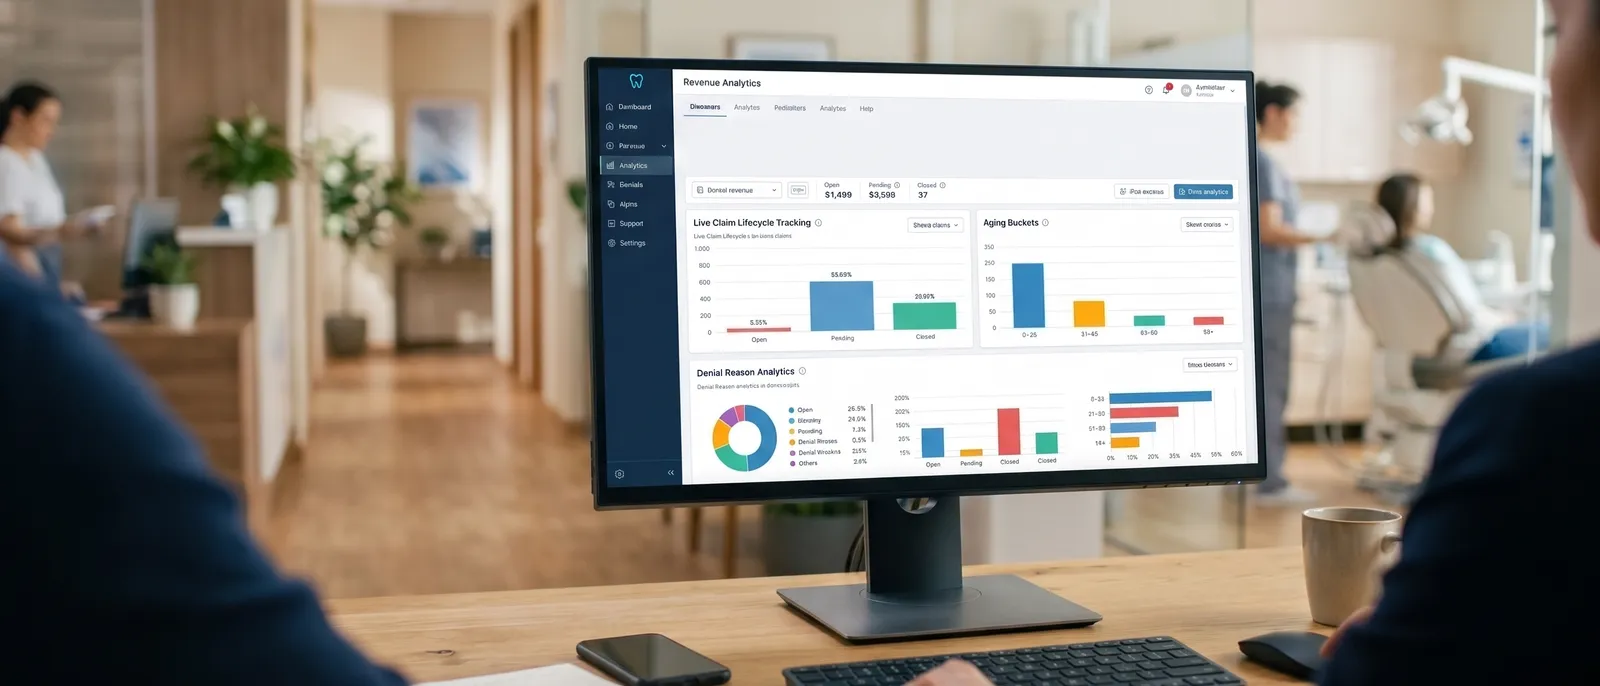
Claims worked every day, not every month
Claim follow-up and A/R recovery across five locations, worked directly inside each practice's existing Dentrix Ascend environment.

What is dental revenue cycle management?
Dental revenue cycle management is the work of making sure a practice gets paid fully and on time for the care it delivers. It follows each patient visit from the booking to the final payment, and covers checking benefits, submitting the claim, following it up, reworking denials, posting the payment and watching the aging report. When people say dental RCM, they mean that whole chain rather than only the claim that goes out in the middle.
What dental RCM services actually include
Revenue cycle management is every step between a patient booking and the practice being paid in full: verification before the visit, coding and documentation at the chair, claim submission, follow-up, denial rework, payment posting, patient statements and the aging report that measures how well all of it went. Most vendors who say RCM mean the middle of that chain. The front and the back are where the money is actually lost.
| Stage | What goes wrong when nobody owns it | Who owns it with us |
|---|---|---|
| Verification | Treatment presented against benefits nobody confirmed | Our insurance verification team, ahead of the schedule |
| Coding and documentation | Claims sent without the narrative or attachments the code requires | Your clinical team codes; we check the claim against payer requirements before it goes |
| Submission | Claims batched weekly instead of sent daily | Us, every day |
| Follow-up | Claims nobody chases until they are past timely filing | Us, on a fixed cycle |
| Denials | Denials written off instead of corrected and resubmitted | Us, grouped by reason code |
| Posting | Payments and adjustments posted late or to the wrong line | Us, as remittances arrive |
| Aging | A report printed monthly and read by nobody | Us, worked bucket by bucket; see A/R recovery |
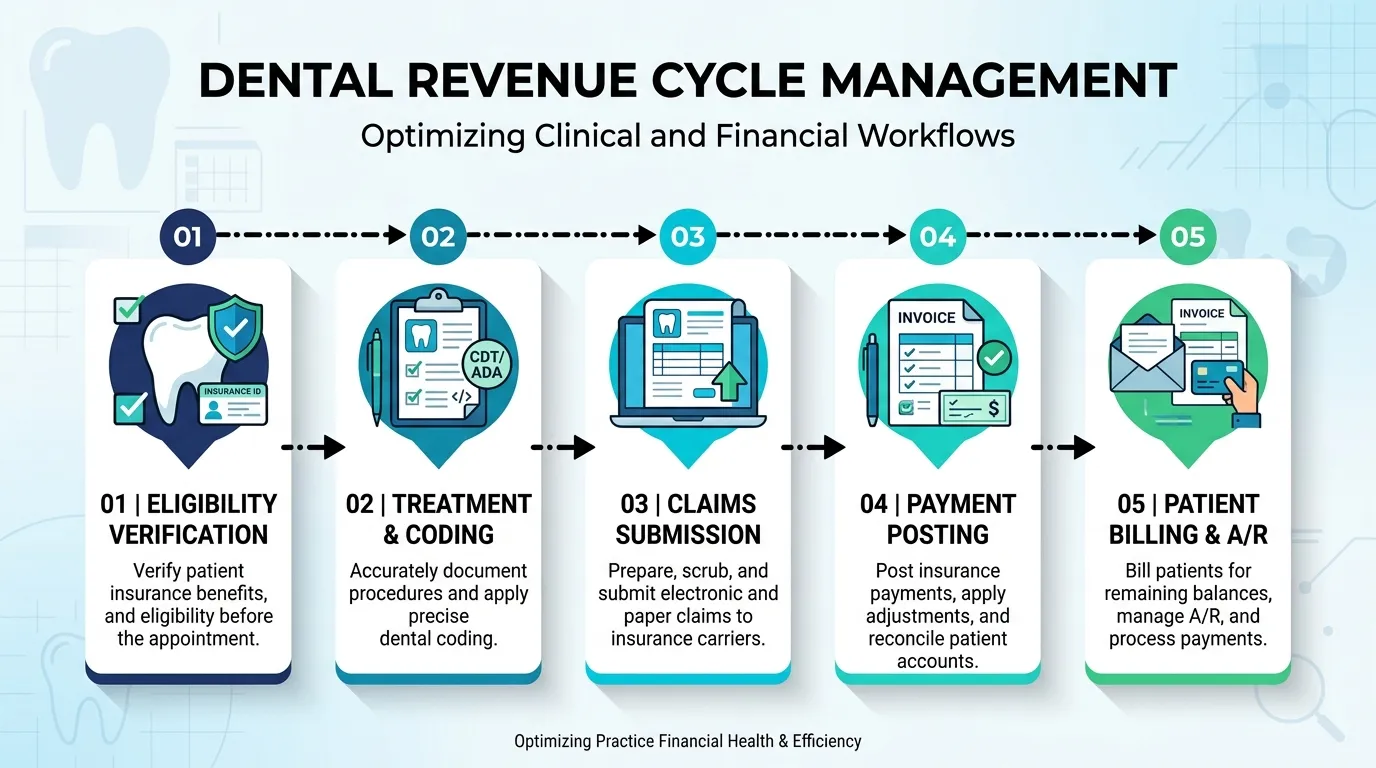
The steps of the dental revenue cycle, in the order they fail
- Benefits are assumed rather than verified, so the claim is right but the patient's estimate is wrong.
- A code is billed without what the payer needs to pay it: an x-ray for a crown, perio charting for scaling and root planing, a narrative for anything by report.
- The claim goes out and nobody looks at it again until the patient asks why they received a bill.
- The denial arrives, gets read as a final answer, and is adjusted off.
- The payment is posted without checking it against the fee schedule, so underpayments look like payments.
Each of those is a step a practice already knows it should do. They fail because they are interruptible work done by people who are interrupted all day. Our guide to why dental claims get denied goes through the denial reasons in detail.
How to reduce days in A/R
Days sales outstanding, or days in A/R, is the average time between a visit and the money arriving. It is the best single number for the health of a practice's revenue cycle, because it moves when any stage slows down. It comes down by doing four things consistently rather than one thing heroically:
- Submit every claim the day of service, with its attachments, rather than in a weekly batch.
- Follow up every unpaid claim on a fixed cycle, starting well before the payer's typical turnaround has passed rather than after the patient calls.
- Rework denials within days of receipt, while the documentation is fresh and the appeal window is wide.
- Collect the patient's portion at the visit, which only works if the estimate was right, which only works if verification was done.
What you see while we do it
Every claim we touch is visible in your own practice management system, because that is where we work. On top of that you get a dashboard showing each claim's status, the claims sitting past ninety days, and denials grouped by payer and by reason code, so you can see which payer and which code costs you the most. It is the same view we run the work on, including the parts that make us look slow.
Outsourced RCM versus a billing hire
One experienced biller in-house is the right answer for some practices, especially single locations with a narrow payer mix and someone who can cover when that biller is out. Outsourcing tends to win when there are several locations to keep consistent, when the aging report keeps growing despite a capable team, or when the practice has been through two or three billers in as many years. Our in-house versus outsourced cost comparison puts real salary data against it, and the calculator lets you run your own numbers.
Common questions
Anything else, ask on the call. We would rather answer it there than guess here.
How much do dental billing companies charge?
The market generally prices one of three ways: a percentage of collections (commonly 2 to 6%), a flat monthly fee per location, or an hourly/FTE rate. Percentage pricing aligns incentives but gets expensive as you grow; flat fees are predictable and usually better for multi-location groups. Ask any vendor which model they use and what happens when your collections increase.
Do you replace our biller or work alongside them?
Either. Some practices hand over the whole function; others keep an in-office lead and use us for follow-up and A/R, which is the part that gets squeezed out by day-to-day interruptions.
Which practice management systems do you work in?
Any of them. Scheduling, insurance verification, claims and posting follow the same steps in every practice management system, so our team works inside whichever one you already run. Nothing is migrated and your team keeps working the way it does today.
How fast can you start?
Onboarding is mostly access, credentialing and learning your payer mix and fee schedules. We deliberately start narrow (one location or one workstream) so you can judge the work before expanding it.
What happens to our old A/R?
It gets worked as a separate backlog track alongside current claims, oldest and largest first. Aged A/R and current claims compete for the same hours, which is exactly why in-house teams rarely clear the backlog.